
Do Dentists Go to Medical School?

It is one of the most common questions people ask about dentistry as a profession, and the answer is shorter than most people expect. Dentists do not go to medical school. They go to dental school, which is its own separate four-year doctoral program with its own admissions process, its own board exams, and its own licensing path. But the two programs overlap far more than most people realize, and there is one situation where a dentist genuinely does earn a medical degree. Here is how the whole thing actually works.

Short answer

No. Dentists attend dental school, not medical school, and earn either a DDS or a DMD. Those two degrees are equivalent. The first couple of years of dental school cover much of the same biomedical science as medical school, sometimes in the same classrooms, before dental students move into clinical training focused on the mouth, teeth, and jaws. The one real exception is oral and maxillofacial surgery, where some residency programs award a medical degree alongside the dental one.

Do Dentists Go to Medical School? What They Do Instead

The route into dentistry is closer to medicine than most people assume, it just branches at a different point.

  1. A bachelor’s degree. Usually four years, with prerequisite coursework in biology, chemistry, organic chemistry, and physics. There is no required major, though most applicants come from the sciences.
  2. The Dental Admission Test. Dentistry’s equivalent of the MCAT, covering natural sciences, reading comprehension, quantitative reasoning, and a perceptual ability section that tests spatial reasoning. That last part is unique to dentistry, for reasons that become obvious the first time you work inside a mouth.
  3. Dental school. Four years, ending in a DDS or DMD.
  4. Board examinations and licensure. National written examination plus a clinical examination, with specific requirements set by the state where you plan to practice.
  5. Optional residency. More on this below, because it is where dentistry and medicine differ most.

Total time from starting college to practicing as a general dentist is typically eight years. For a physician, it is usually eleven or more once residency is included.

 DentistryMedicine
Admission testDental Admission Test, including a perceptual ability sectionMCAT
Degree awardedDDS or DMD — equivalent to each otherMedical degree
Professional schoolFour yearsFour years
ResidencyOptional for general dentistryMandatory, typically three to seven years
Time from starting college to practicingAbout eight yearsUsually eleven or more

DDS or DMD: Is There a Difference?

No. This trips people up constantly, so it is worth being clear.

DDS stands for Doctor of Dental Surgery. DMD stands for Doctor of Dental Medicine. They are the same degree, representing the same education and the same scope of practice. Which one you receive depends entirely on which school you attended, because individual universities chose different names historically. A dentist with a DMD and a dentist with a DDS completed equivalent training and can do exactly the same work.

If you are a patient comparing two dentists, the letters after their names tell you nothing about their skill or their focus. What they have studied since graduating tells you far more.

Where Dental School and Medical School Overlap

Here is the part that surprises people. The first half of dental school looks a lot like the first half of medical school.

Dental students study anatomy, physiology, biochemistry, microbiology, pathology, and pharmacology. At many universities, dental and medical students sit in the same lectures for some of these courses, taught by the same faculty. The reasoning is straightforward: the mouth is connected to the rest of the body, and you cannot treat it safely without understanding the whole patient.

That matters in practice more than people think. A dentist needs to understand how a patient’s blood pressure medication affects bleeding, how uncontrolled diabetes affects healing, how a heart condition changes what anesthetic is appropriate, and which medications interact with what they are about to prescribe. Dentists are the ones who often spot signs of systemic disease first, because they are looking inside the body on a regular schedule.

Where the paths split is the second half. Medical students rotate through specialties across the entire body. Dental students move into clinical training concentrated on the teeth, gums, jaws, and surrounding structures, and they start treating patients under supervision.

The One Case Where Dentists Do Go to Medical School

Oral and maxillofacial surgery is the genuine exception.

These are the surgeons who handle wisdom teeth, dental implants, corrective jaw surgery, facial trauma, and reconstruction. Their training is long, and some residency programs are structured as dual-degree tracks where the resident earns a medical degree in addition to their dental degree, and completes a general surgery internship as part of the program.

So a dentist who went to medical school is almost always an oral surgeon who took that route. It is a real path, it is just a specific one, and it is not what happens for the vast majority of dentists.

Residency: Required in Medicine, Optional in Dentistry

This is the biggest structural difference between the two professions, and it is the one most people miss.

In medicine, residency is mandatory. A newly graduated physician cannot practice independently and must complete a residency, typically three to seven years depending on the field.

In dentistry, a graduate can be licensed and practice general dentistry without a residency. Many choose to complete an optional additional year, usually a general practice residency or an advanced education in general dentistry program, to build confidence and experience. But it is not required.

Residency is required for the recognized dental specialties, which include orthodontics, oral and maxillofacial surgery, periodontics, endodontics, prosthodontics, pediatric dentistry, and several others. Those programs run two to six years beyond dental school depending on the specialty.

What Dental School Does Not Cover

Dr. Tejas Patel at his desk, reflecting the continuing education that builds cosmetic dentistry skills after dental school
Most procedure-specific skill is built after graduation, deliberately, one subject at a time.

Because a general dentist can practice straight out of school, dental school has to cover an enormous amount of ground in four years. Something has to give, and what tends to give is depth in the elective, procedure-specific areas.

Cosmetic dentistry is the clearest example. It is not a recognized dental specialty, which means there is no residency for it. Any licensed general dentist can legally offer cosmetic procedures including veneers, including no prep and prepless techniques. But most dental programs cover them lightly, often with limited hands-on experience before graduation. Plenty of dentists finish school having never prepped or delivered a veneer case.

That gap is why continuing education exists. Dentists are required to complete continuing education to maintain licensure, with the specific hours set by each state, and it is where most of the procedure-specific skill in a dentist’s career actually gets built. Not in school. Afterwards, deliberately, one subject at a time.

I went through this myself. Learning cosmetic dentistry properly took me years of courses, a lot of research, and a real amount of money on top of what dental school already cost. The knowledge was out there. It just was not in the curriculum.

Key Takeaways

  • Dentists do not attend medical school. They complete a separate four-year dental program.
  • DDS and DMD are equivalent degrees. The difference is which school awarded it, nothing more.
  • The first years of dental school overlap heavily with medical school, sometimes in the same classrooms.
  • Oral and maxillofacial surgery is the exception, where some residencies award a medical degree too.
  • Residency is mandatory in medicine and optional for general dentistry.
  • Cosmetic dentistry is not a recognized specialty, so no residency exists for it.
  • Procedure-specific skills like veneers are usually built through continuing education after graduation.

Action Items

If you are considering dentistry as a career:

  • Check the prerequisite coursework for the schools you are interested in early, since requirements vary.
  • Shadow a general dentist and a specialist. The day-to-day work differs enormously between them.
  • Take the perceptual ability portion of the admission test seriously. It measures something the other sections do not.
  • Ask any dentist you shadow what they had to learn after graduating. The answers are usually revealing.

If you are already practicing:

  • List the procedures patients ask you for that you currently refer out. That list is your continuing education roadmap.
  • Check your state’s continuing education requirements and confirm which credits count toward them.
  • Pick one procedure to get genuinely good at this year rather than sampling several.
  • Track which cases make you uncomfortable. Discomfort usually points at a specific gap, not a general one.

Frequently Asked Questions

Yes. A DDS or DMD is a doctoral degree, and dentists are doctors within their scope of practice. They are not physicians, which is a different degree and a different scope.

Usually eight years after high school: four years of undergraduate study and four years of dental school. Specialties add another two to six years of residency on top of that.

They are difficult in different ways. The academic load in the early years is comparable, and dental school adds a significant hands-on technical component early on, because dentists perform procedures from the start of their clinical training.

Yes, within the scope of dental practice. That typically covers antibiotics, pain medication, and other drugs related to dental treatment, which is one reason pharmacology is part of the curriculum.

Usually only at an introductory level. Coverage varies by program, and many graduates have limited or no hands-on veneer experience. Most dentists who offer veneers learned the procedure through continuing education after graduating.

Not in the sense of a recognized specialty, because cosmetic dentistry is not one. Any licensed general dentist can offer cosmetic procedures. What differentiates them is the training they have pursued and the experience they have built, which is worth asking about directly.

Conclusion

So, do dentists go to medical school? No, but the training is closer to medicine than the separate name suggests, and the two paths share a foundation before splitting toward different parts of the body. The more interesting part of the answer is what happens after graduation. Because general dentists can practice without a residency, and because cosmetic dentistry has no specialty track at all, the skills a dentist offers ten years in are largely the ones they went out and learned on purpose.

If veneers are on that list for you, the Veneer Blueprint Course covers the full process from case selection through bonding, the way I wish it had been laid out for me when I was starting. You can see how the courses are structured on the courses page, and the CE information page explains how the credits work.
Anterior Veneer Prep: Getting the Preparation Right

Most veneer cases that disappoint were decided before the porcelain was ever made. Anterior veneer prep is where a case is set up to succeed or quietly set up to fail, and the mistakes are rarely dramatic. A little too much reduction here, a margin in the wrong place there, and a preparation cut to the tooth in front of you instead of to the result you were trying to create.

Short answer

Design the final result first, then prepare to that design rather than to the existing tooth. Stay in enamel wherever you can, because bonding to enamel is substantially more predictable than bonding to dentin. Use depth cuts through a mock-up so your reduction is measured from where the veneer will actually sit. Keep margins on enamel with a defined chamfer, round every line angle, and reduce the minimum the case genuinely requires. When the teeth are already undersized or retruded, minimal or no preparation may be the correct answer.

Design First, Cut Second

The single biggest shift in thinking for dentists new to veneers is that preparation is not something you do to a tooth. It is something you do relative to a plan.

If a tooth already sits where the final veneer needs to be, you may remove very little. If it is rotated or protrusive, you may remove more from one area and almost nothing from another. Cutting a uniform amount off every tooth ignores that, and it is how enamel gets removed that the case never needed.

The practical sequence most cosmetic dentists settle on is: diagnostic wax-up, intraoral mock-up from that wax-up, evaluate it with the patient, then prepare through the mock-up. Preparing through the mock-up means your depth cuts are measured from the surface of the planned result rather than from the existing tooth, which is what keeps reduction honest.

It also gives you a check you cannot get another way. If a depth cut through the mock-up barely touches the tooth underneath, that tooth needed almost no reduction, and now you know.

The Rule That Matters Most: Stay in Enamel

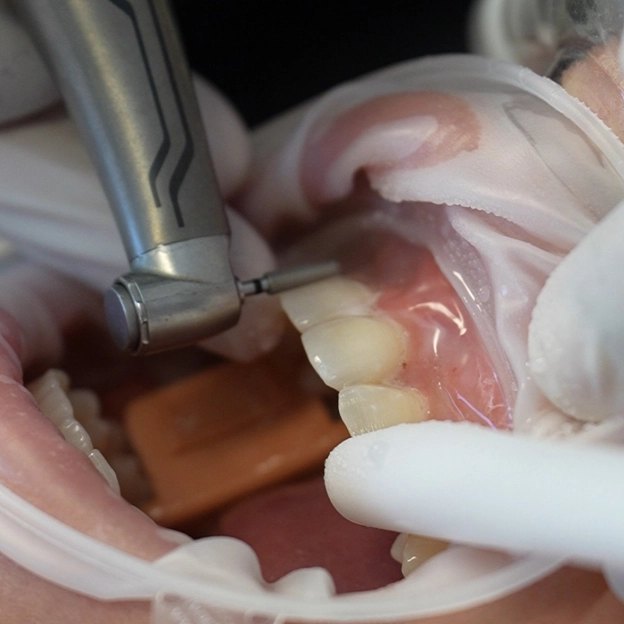
Handpiece reducing an anterior tooth during veneer preparation, with the lip retracted and the margin visible at the gingival third
The cervical third is where enamel is thinnest and where the bur most easily takes more than the case needed.

If you take one thing from this, take this.

Bonding to enamel is considerably more predictable and more durable than bonding to dentin, and veneers bonded predominantly to enamel have a strong long-term track record. Once a preparation moves substantially into dentin, bond reliability drops, sensitivity risk rises, and the margin gets harder to seal.

Enamel on anterior teeth is thinnest at the cervical third, which is exactly where over-reduction most commonly happens, because the bur wants to dig in as it follows the emergence profile. Conservative cervical reduction is not timidity. It protects the part of the preparation you most need to be enamel.

Anterior Veneer Prep: Reduction by Zone

Anterior teeth are not uniform, and reduction should not be either. Facial reduction is usually described in three zones, with the least at the gingival third and the most at the incisal third.

ZoneReductionWhat drives it
Gingival thirdLeastEnamel is thinnest here, and it is where over-reduction most commonly happens as the bur follows the emergence profile. It is also where the margin most needs enamel underneath it.
Middle thirdSlightly moreClearance through the body of the tooth is what lets the ceramist control contour instead of overbuilding it.
Incisal thirdMostMore again toward the incisal, with additional reduction if the edge is being shortened or covered. Covering it brings the occlusion into the plan.

Commonly taught ranges land around a few tenths of a millimeter cervically, slightly more through the body of the tooth, and more again toward the incisal. Exact figures vary between protocols and by the ceramic being used, so use the numbers your ceramist and your material actually require rather than a general figure from an article.

Two tools make this controlled rather than estimated.

Depth cutting burs create grooves at a known depth so you are reducing to a measured target instead of judging by eye. Place them through the mock-up, then join and smooth between them.

A silicone reduction guide sectioned from the wax-up lets you verify clearance at any point. Checking partway through beats discovering at the impression stage that one tooth is short.

Under-reduction causes its own problems, and they are less obvious. Insufficient clearance forces the ceramist to make the veneer too thin to mask what is underneath, or to overbuild the contour, and an overcontoured anterior veneer looks bulky no matter how good the ceramics are.

Margin Design and Placement

A defined chamfer margin is standard, giving the ceramist a clear finish line and the porcelain adequate thickness at the edge. Avoid a feathered or indistinct margin, which is difficult to read on a die and difficult to seat accurately.

On placement, equigingival or slightly supragingival margins are easier to isolate, easier to capture accurately, easier for the patient to keep clean, and kinder to the tissue over time. Where the underlying tooth is discolored, or where the case requires the margin to disappear entirely, a slight intracrevicular placement may be justified.

Treat subgingival placement as a decision with a reason rather than a default, since deeper margins mean harder isolation and isolation protects your bond. Keep the margin on enamel wherever the case allows, because a margin ending on dentin or root surface seals less well and is more likely to stain at the interface over time.

Incisal Edge and Interproximal Decisions

Two design choices deserve deliberate thought rather than habit.

The incisal design. The main approaches are leaving the incisal edge untouched, finishing at a butt joint, or covering the incisal and wrapping slightly onto the palatal. Covering the incisal gives the ceramist more control over length and edge characterization, which matters when you are lengthening teeth. It also requires more reduction and brings the occlusion into the conversation, since the porcelain now sits where the patient functions. Whichever you choose, avoid leaving unsupported enamel at the incisal edge.

The interproximal extension. How far you carry the preparation into the embrasure depends on what you are correcting. Diastema closure, significant shade change, or reshaping the outline generally require extending further so the transition is hidden. Cases where the existing form is close to target can stay conservative. Too little leaves a visible junction. Too far removes enamel you did not need.

Common Prep Mistakes

  • Preparing to the tooth instead of to the plan. The most consequential error, and the one that causes most of the others.
  • Over-reduction at the cervical third. Where enamel is thinnest and where the margin needs enamel most.
  • Under-reduction leading to bulky contours. The ceramist cannot solve a clearance problem, only compensate for it visibly.
  • Sharp line angles and a rough surface. Sharp internal angles concentrate stress in the porcelain and make seating less predictable. Every transition should be smooth and rounded, and the preparation free of gouges, which also makes it scan and photograph cleanly for the ceramist.
  • Indistinct margins. The ceramist has to guess where the veneer ends.
  • Ignoring occlusion when covering the incisal. The porcelain is now in function and needs to be planned for.
  • Skipping the reduction guide. Checking clearance at the end is checking too late.

When Less Preparation Is the Right Answer

Not every case needs conventional preparation. Teeth that are already small, worn, retruded, or spaced may need very little reduction or none, and preparing them anyway removes enamel for no clinical benefit.

Minimal prep, no prep, and prepless approaches are a real category rather than a marketing idea, and they are only appropriate for the right case. Attempting them on teeth that are already full or protrusive produces exactly the overcontoured result they are supposed to avoid. Case selection is what separates the two outcomes, which is why the decision about how much to prepare belongs in treatment planning rather than at the handpiece. Both approaches carry CE credit when studied formally.

Key Takeaways

  • Prepare to the planned result, not to the existing tooth, using a wax-up and mock-up.
  • Staying in enamel is the most important factor in long-term bond reliability.
  • Enamel is thinnest cervically, which is where over-reduction most often happens.
  • Use depth cuts through the mock-up and verify with a silicone reduction guide.
  • Under-reduction causes bulky contours the ceramist cannot fix.
  • A defined chamfer at or slightly above the tissue is easier to isolate and seal.
  • Covering the incisal edge gives more control but brings occlusion into play.
  • Some cases genuinely need minimal or no preparation, and that is a planning decision.

Action Items

  • On your next anterior case, do a wax-up and an intraoral mock-up before touching a tooth, even if you feel you could prep it without one.
  • Add depth cutting burs to your veneer setup if they are not already there, and place your cuts through the mock-up.
  • Make a silicone reduction guide from your wax-up and check clearance halfway through the preparation rather than at the end.
  • Photograph your finished preparations for the next several cases and review them against your own margin and line angle standards. Compare them side by side.
  • Ask your ceramist what minimum thickness they want for the material you are using, and prepare to that number rather than a generic one.
  • Review your last few cases and note whether your margin placement was a decision or a habit.

Frequently Asked Questions

Less than most people assume, and it varies by zone and by case. Reduction is greatest toward the incisal and least at the gingival third, and a well-planned case removes only what the final contour requires. Some cases need very little.

Only when there is a reason, such as masking significant discoloration. Margins at or slightly above the tissue are easier to isolate, capture, and clean, and isolation directly affects your bond quality.

It removes less tooth structure by definition, but it is only conservative in outcome if the case suits it. On teeth that are already full or protrusive, adding porcelain without reduction produces an overcontoured result, so suitability is determined during planning.

Conclusion

Good anterior veneer prep is mostly restraint applied in the right places. Plan the result, measure reduction from that result, protect enamel especially at the cervical, and give the ceramist a clean, defined preparation. The dentists whose cases look consistently good are rarely doing something exotic at the handpiece. They are doing the planning that makes the preparation obvious.

Preparation is far easier to understand once you have watched it done and heard the reasoning at each step. The Veneer Blueprint Course covers preparation design within the full workflow, from case selection through temporaries and bonding. If your cases lean toward conservative approaches, the No Prep and Prepless Veneers Course goes deeper there, and both are outlined on the courses page.

How to Become a Cosmetic Dentist

If you are looking for the residency program that turns a dentist into a cosmetic dentist, there isn’t one. That surprises a lot of people, including dentists, and it changes the whole answer to how to become a cosmetic dentist. There is no board to sit, no specialty track to match into, and no title anyone hands you. What exists instead is a set of skills you go out and build on purpose, in a particular order, after you already have your license. Here is what that actually looks like.

Short answer

Finish dental school, get licensed, then build cosmetic skills through continuing education, because cosmetic dentistry is not a recognized dental specialty and has no residency. The skills that matter most are case selection, smile design, occlusion, photography, preparation design, and bonding. Start with small cases, photograph everything, build a relationship with a good ceramist, and add complexity gradually. Most dentists take years to get genuinely comfortable, and that is normal.

First, an Important Clarification

Cosmetic dentistry is not one of the recognized dental specialties. Orthodontics is. Periodontics is. Oral and maxillofacial surgery is. Cosmetic dentistry is not, which has two consequences worth understanding before you plan anything.

The first is that any licensed general dentist can legally offer cosmetic procedures, including veneers, without additional credentials. Nothing is stopping you, which is either encouraging or alarming depending on how you look at it.

The second is that because nothing is required, nothing is provided either. No structured curriculum hands you the skills in a sensible sequence. You assemble that yourself, and the dentists who do it well are deliberate about the order.

The Baseline You Need First

Everything below assumes the standard path is done or in progress.

  1. Dental school. Four years, ending in a DDS or DMD. The two are equivalent.
  2. Licensure. Board examinations plus whatever your state requires.
  3. Optional residency. A general practice residency or advanced education in general dentistry year is not required, but the extra clinical volume helps, particularly if your school’s clinical experience was thin.

If you are still in school, get your hands on as much restorative work as possible and start photographing your cases now. Nobody regrets having early photos.

How to Become a Cosmetic Dentist: The Skills That Matter

This is the part that matters, and it is longer than most people expect.

SkillWhy it matters
Case selectionThe most important cosmetic dentistry skill and the least discussed. Knowing which cases to accept, which to refer, and which to decline entirely prevents more problems than any technique. A beautiful veneer case on a patient who needed orthodontics first is still a failed case.
Smile designUnderstanding tooth proportion, midline, incisal edge position, smile line, and how the gingival architecture frames everything. This is design work, and it is learnable.
Facially driven planningDesigning the smile to fit the face rather than designing teeth in isolation. Treating the teeth as the whole picture is how cases end up technically correct and visually wrong.
OcclusionUnderrated, and the reason a lot of otherwise good cosmetic work fails. Porcelain does not forgive a bite you did not account for.
PhotographyA standardized photo series is how you communicate with your ceramist, plan, track your progress, and document what you did. Most dentists who plateau are not photographing consistently.
Shade selection and lab communicationThe best preparation will not save a case where the ceramist did not have what they needed. Communicating what you want, in the terms a lab actually uses, is its own discipline.
Preparation designUnderstanding conventional prep, minimal prep, and no-prep and prepless approaches, and knowing which situation calls for which. Over-preparation is one of the most common and least reversible mistakes in the field.
ProvisionalsTemporaries are not a placeholder. They are the test drive for the final result, and the chance to get feedback before anything is permanent.
Bonding protocol and isolationThis is where cases are won or lost. Consistency here separates predictable results from occasional ones.
MaterialsKnowing what different ceramics do, where each performs, and what each needs in thickness and bonding.
Patient communicationUnderstanding what a patient actually wants and being honest about what is achievable. A clinically excellent case can still disappoint if the conversation up front was vague.

How to Build Those Skills

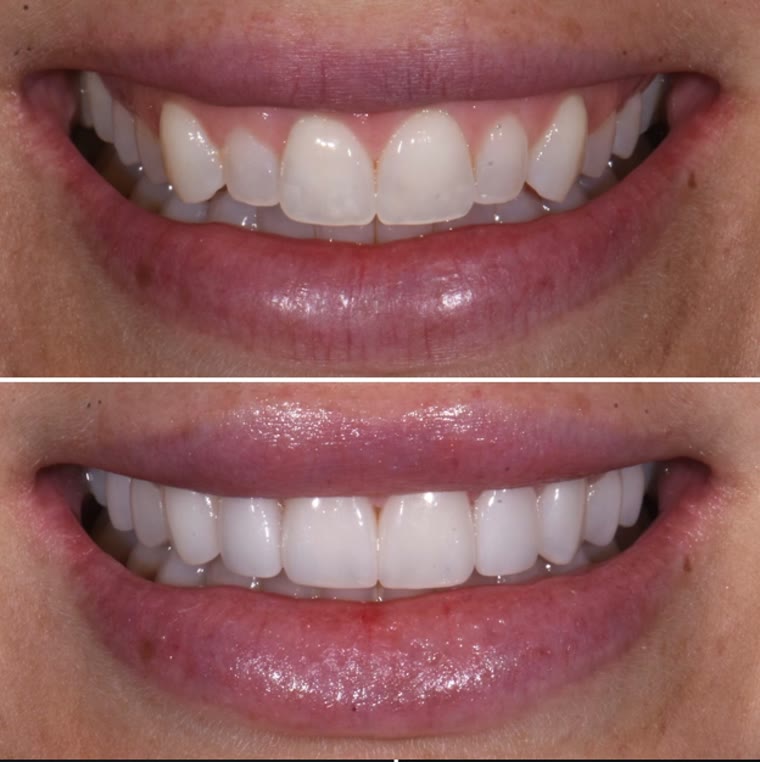
Before and after photographs of a porcelain veneer case, showing the standardized documentation series a cosmetic dentist builds for every patient
A consistent before-and-after series is how you communicate with your lab and assess your own work.

Continuing education is the mechanism, since that is where procedure-specific training lives. You complete continuing education to maintain licensure anyway, so the real question is what you point those hours at.

A few things that help more than others:

  • Learn in sequence. The full workflow first, then specific techniques. Studying bonding chemistry in depth before you understand case selection is learning the fifth step first.
  • Watch the procedure, not just the slides. Seeing a case done start to finish, with the reasoning narrated, transfers far more than a written description of the same steps.
  • Find a ceramist and stay with them. Your lab relationship affects results more than most material choices, and consistency lets you both calibrate.
  • Start smaller than your ambition. Two or four units before ten. Confidence built on completed cases holds up. Confidence built on courses alone does not.
  • Document everything. Before, provisional, and after, in a consistent series. Your own cases are the best teaching material you will ever have access to.
  • Get your work looked at. Study clubs, mentors, or peers who will tell you what is wrong rather than what is nice. Improvement requires someone pointing at what you cannot see.

When I was starting out, this took me years of courses and considerable money on top of what dental school had already cost. The information existed. It was just not organized anywhere, and I spent a long time assembling it piece by piece.

Mistakes That Slow People Down

  • Starting with a large case. A ten-unit case as your first veneer experience is a lot of exposure for a technique you are still learning.
  • Skipping occlusion. The most common source of failures that appear months later.
  • Over-preparing. Enamel you remove does not come back, and bonding to enamel is better than bonding to dentin.
  • Chasing shade instead of design. A well-designed case in a slightly different shade reads better than a perfectly shaded case with wrong proportions.
  • Not photographing. No photos means no lab communication, no self-assessment, and no record.
  • Saying yes to the wrong patient. Expectations that were never realistic do not become realistic after treatment.
  • Collecting courses without doing cases. Courses shorten the path. They do not replace the cases.

Key Takeaways

  • Cosmetic dentistry is not a recognized specialty, so there is no residency and no required credential.
  • Any licensed general dentist can legally offer cosmetic procedures, which means the standard you hold yourself to is your own.
  • Case selection matters more than technique, and knowing when to decline prevents most problems.
  • Occlusion and photography are the two most commonly skipped fundamentals.
  • Over-preparation is among the least reversible mistakes in the field.
  • Progress comes from doing cases consistently between courses, not from courses alone.

Action Items

  • Set up a standardized photo series and start using it on every anterior case, starting with your next patient.
  • Write down the last five cosmetic cases you referred out and identify what specifically stopped you from doing them.
  • Choose one ceramist and commit to them for your next several cases instead of shopping around.
  • Pick the smallest cosmetic case on your schedule this month and treat it as a deliberate practice case, fully documented.
  • Audit your continuing education hours and check how many went toward a skill you actually use.
  • Find one person whose work you respect and ask them to critique a finished case honestly.

Frequently Asked Questions

Eight years to become a dentist, then a variable period building cosmetic skills. Most need years of consistent case work before full smile makeovers feel comfortable, though simpler cosmetic cases come much sooner. Nobody gets there in a weekend, and anyone suggesting otherwise is selling something.

No, because cosmetic dentistry is not a recognized specialty. Be aware that some state dental boards have rules about how dentists may advertise areas of focus, so check your own board’s language requirements.

Yes. Any licensed general dentist can legally place veneers. Whether they should on a given case depends on their training and the complexity of the case, which is a judgment call rather than a legal one.

Case selection and smile design fundamentals, then the full workflow start to finish, then individual techniques. Understanding how a case comes together makes each technique easier to place in context.

No, and experienced general dentists often pick this up quickly. You already have hand skills, patient management, and clinical judgment. What you need is the specific workflow, a shorter distance than it looks from the outside.

Very. The ceramist is a partner in the result, not a vendor filling an order. Consistency with one good lab, and learning to communicate in the terms they use, improves outcomes considerably.

Conclusion

How to become a cosmetic dentist comes down to something less dramatic than a credential. You get licensed, then you build a specific set of skills dental school did not have time to give you, in a sensible order, while doing cases the whole way through. Nobody is going to structure that for you, which is the hard part and also why a dentist who does structure it can move quickly.

If veneers are the piece you want to get right, the Veneer Blueprint Course walks through the full sequence, from case selection and smile design through preparation, temporaries, and bonding, in the order I wish someone had laid out for me. Dentists already comfortable with veneers usually find the No Prep and Prepless Veneers Course the better next step. Both are compared on the courses page, and the CE information page covers how the credits work.

How Patients Choose a Cosmetic Dentist (And How to Position Yourself as the Best Choice)

One of the most important parts of growing a cosmetic practice is understanding how patients actually choose their cosmetic dentist. Patients investing in veneers heavily research, compare, and evaluate. When you understand their decision-making process, you can better position your practice and increase high-value case acceptance.

  1. Your Esthetic Style Is Your Brand
    Patients look for a dentist with a clear, consistent esthetic style natural, bold, glamorous, minimalistic, etc.
    Your photo gallery should reflect your artistic approach, showing a variety of cases customized to each patient’s facial features.
  2. Communicate Experience Clearly
    Patients want specifics:
    • How many veneer cases you do
    • How long you’ve focused on cosmetics
    • Whether you do all the work yourself
    • How predictable your results are

      Your expertise should be obvious from your online presence, reviews, and consultation process.
  3. High-Quality Before & Afters Build Confidence
    Your photo portfolio is your résumé. Patients want to see:
    • Large case volume
    • Different smile styles
    • Cases similar to theirs
    • Consistent quality

      Good documentation and photography elevate trust.
  4. Consultations Should Educate, Not Sell

    This is where patients decide if they trust you. Collaborative consultations virtual or inperson help patients feel understood and supported. They should leave more informed, notpressured.
  5. Reviews & Social Media Are Powerful Proof
    Cosmetic patients research deeply. Strong reviews and an authentic social media presence helpthem understand:
    • Your results
    • Your chairside manner
    • Your office vibe
    • How predictable your outcomes are

      Social content is often the first step in the patient journey
  6. Smile Previews Increase Case Acceptance
    Wax-ups, mock-ups, or digital smile designs help patients visualize the outcome and build confidence in your process.
  7. Financing and Clear Fees Matter
    Cosmetic dentistry is an investment. Offering financing options or payment plans can remove barriers and make treatment more accessible without discounting
  8. Your Lab & Team Reflect Your Quality
    Elite ceramists, high-quality materials, and a well-trained team significantly impact the final result. Patients notice consistency and professionalism.
  9. Patients Take Their Time Support the Process
    Choosing a cosmetic dentist is emotional and expensive. When you educate clearly, communicate well, and showcase predictable results, the right patients will choose you with confidence.

For Dentists Looking to Elevate Their Cosmetic Skills

If you want to build a predictable, high-end cosmetic practice, the Veneer Blueprint Course teaches the systems, workflows, prep guidelines, design principles, and case selection methods I use every day.

How Do Lip Fillers Interact With Veneers? What Dentists Should Know

As cosmetic dentistry continues to overlap with facial esthetics, more patients are combining veneers with lip fillers to enhance their smile and overall facial harmony. Understanding how these two treatments influence one another is essential for predictable esthetic outcomes.

Why Lip Position Matters in Smile Design

The lips act as the frame of the smile. Their volume, curvature, and resting position directly influence:

  • Tooth display at rest
  • Tooth display during a full smile
  • Ideal tooth length and proportion
  • Smile arc and incisal edge position
  • Perceived symmetry and balance

Because of this, any changes to lip volume whether increasing or decreasing can alter how much tooth structure is visible and how the smile is perceived.

Impact of Lip Fillers on Veneer Design

When designing veneers, clinicians assess:

  • Resting lip position
  • Full smile dynamics
  • Vertical tooth display
  • Smile width and fullness

Lip fillers can influence all of these.

Example considerations:

  • More lip fullness may reduce visible tooth length at rest.
  • Less lip volume may increase tooth display.
  • A fuller upper lip can alter the aesthetic balance and the ideal incisal edge position.
  • Filler can slightly change the curvature or mobility of the lip, affecting smile dynamics.

Patients often choose veneers because they want to show more teeth when they smile, but lip fillers can either help or hinder that goal depending on timing and volume.

What Should Patients Do?

Encourage every patient to tell you if they:

  • Already have lip fillers
  • Recently dissolved filler
  • Plan to get fillers after receiving veneers
  • Are unsure about future lip esthetic treatments

This information helps you design a smile that works with their facial esthetics not against it.

Clinical Recommendations

For best results:

  • Take records after fillers have settled (typically 2+ weeks).
  • Discuss how changes in lip volume may affect final smile display.
  • Reevaluate smile design if the patient plans future lip augmentation.
  • Document tooth display at rest and during smile carefully these measurements may shift post-filler.

Bottom Line

Lip fillers and veneers can complement each other beautifully when planned together. The key is communication: Always know if a patient has fillers or plans to get them so you can deliver the most harmonious, predictable esthetic outcome.

Want More Clinical Tips for Veneers?

For deeper training on smile design, tooth display analysis, case planning, and esthetic workflows, explore the Veneer Blueprint Course designed specifically for dentists who want predictable, high-end cosmetic results.

It includes systems, checklists, over-the-shoulder walkthroughs, and real case breakdowns to elevate your veneer cases with confidence.

How Many Veneers Should I Do? A Practical Guide for Dentists

One of the most common clinical questions in cosmetic dentistry is:

“How many veneers are ideal for a predictable, esthetic smile makeover?”

Patients may request 2, 4, 6, 8, 10 or more veneers, but as clinicians, we know the right number
isn’t random it’s strategic.

What Patients Actually Show When They Smile

Most people display 8–10 upper teeth when they smile. Lower tooth display varies widely and depends on lip position, age, and facial esthetics.
Because of this, a full upper smile makeover typically ranges from 8 to 10 veneers, while a full upper-lower transformation may involve 10 upper and 10 lower veneers.

Why 6 Veneers Often Fall Short

Dentists learn early about the Rule of 4 and 8:

  • 4 veneers (centrals + laterals) usually blend well because the canines stay natural and they naturally transition in size and prominence.
  • 8 veneers blend even better because you carry the design through the canines and first premolars.

But 6 veneers?
That’s where blending issues arise

Here’s why:

  • Canines are visually dominant.
  • Premolars and laterals are smaller and create a natural taper.
  • Stopping the veneer count at the canines creates a harder transition visually especially if shade changes or alignment corrections are being made

For these reasons, many cosmetic dentists (myself included) often avoid doing 6 veneers unless the case is very specific

My General Recommendation

For most esthetic smile makeover cases:

  • 4 veneers → Good for localized issues
  • 8 veneers → Best blend for full-smile esthetics
  • 10+ veneers → Ideal when patients show a wide smile or want a full transformation

Want to Master Case Selection, Design, and Execution?

If you want deeper guidance on veneer counts, smile design, case sequencing, and workflow, the Veneer Blueprint Course is the most comprehensive resource I’ve created for dentists.

You’ll learn:

  • How to choose the ideal number of veneers
  • Step-by-step prep and no-prep decision making
  • Systems, checklists, and video walkthroughs
  • How to deliver consistent, high-end cosmetic results

Who Is a Candidate for Veneers? Understanding Why Patients Choose Porcelain Veneers

As dentists, we see a wide variety of motivations behind why patients start considering veneers. Most patients pursue veneers because there’s something about their smile they want to change, refine, or correct. Our job is to understand their goals, evaluate their anatomy, and determine whether veneers are the right solution or if another treatment is more appropriate.

This is where proper case selection becomes the difference between a long-lasting, predictable veneer result… and a case that leads to remakes, complications, or patient dissatisfaction.

Below is a dentist-focused breakdown of who is a candidate, why patients request veneers, and how to classify the smile concerns veneers can address.

Why Patients Consider Veneers

Patients typically begin exploring veneers due to one or more of the following concerns:

  • Smile esthetics that they feel do not match their self-image
  • Color issues that resist whitening
  • Shape and proportion issues
  • Alignment concerns when orthodontics is not desired
  • Wear, chips, or structural changes from aging or parafunction
  • Old dental work that no longer blends or looks natural
  • Desire for long-term white, stable, stain-resistant teeth

Many patients say:

“I just want my smile to look the way I always imagined it could.”

Common Smile Characteristics Seen in Veneer Consultations
Below are categories frequently seen during cosmetic case evaluations:

Tooth Position & Alignment

  • Crowding
  • Gaps or diastemas
  • Crooked teeth
  • Narrow smile
  • Open bite
  • Crossbite (when mild and primarily esthetic)
  • Bite discrepancies with acceptable functional movement

Tooth Proportion & Shape

  • Short teeth
  • Worn-down teeth
  • Uneven edges
  • Chipped teeth
  • Misshapen anatomy
  • Teeth that “don’t show” when smiling

Tooth Color

  • Yellow or dark teeth
  • Grey/brown intrinsic discoloration
  • Deep stains or tetracycline staining
  • Stains resistant to whitening
  • Stains between teeth

Midline & Symmetry Concerns

  • Midline deviations
  • Canting of the smile line
  • Uneven tooth lengths
  • Reverse smile lines

Gum & Soft Tissue Factors

  • Gummy smile
  • Uneven gums

Functional & Restorative Considerations

  • Replacing old esthetic dentistry
  • Managing chipped or breaking teeth
  • Correcting worn enamel due to bruxism
  • Replacing missing teeth (in combination with implants or bridges)

In short:
If a patient wants to improve the color, shape, alignment, proportion, or overall esthetic harmony of the smile and the teeth are structurally sound veneers are an excellent
option.

FAQ

From a clinical perspective, ideal veneer candidates typically have

Stable gingiva with no active inflammation.

For predictable bonding and long-term adhesion.

No untreated functional problems that would jeopardize the veneers.

Understanding the esthetic possibilities and limitations.

No extensive decay, failing restorations, or fracture patterns requiring full-coverage crowns.

No extensive decay, failing restorations, or fracture patterns requiring full-coverage crowns

Patients who want predictable color and minimal maintenance.

Who Is Not a Candidate? (Or Requires Modification First)

  • Patients under 18
  • Patients with poor oral hygiene
  • Patients with active periodontal disease
  • Heavy bruxers without protective protocols
  • Patients needing orthodontics for large functional issues
  • Teeth requiring full coverage instead of partial coverage

Case selection is critical. Veneers are not a “one-size-fits-all” solution they are a precision-driven, diagnosis-based treatment.

The Bottom Line for Dentists

Porcelain veneers can dramatically improve smile esthetics when case selection is done correctly.
If a patient wants to change color, shape, alignment, proportion, symmetry, or display,
veneers remain one of the most effective tools in cosmetic dentistry.

And most importantly:

Veneers work beautifully when the dentist identifies the right patient, the right tooth conditions, and the right goals.

For Dentists Wanting to Master Case Selection

If you want deeper training on veneer evaluation, mock-ups, prep design, workflow, and long-term case success, I break this down step-by-step in my Veneer Blueprint Course including specific modules dedicated entirely to Case Selection, Smile Design, and Treatment Planning for predictable veneer results.

Crowns vs. Veneers: How to Choose the Right Restoration for Each Case

One of the most common questions during cosmetic and restorative consultations is:
“Should this patient get veneers or crowns?”

Both restorations can deliver beautiful esthetics, but they serve different biological, structural,
and functional purposes. As dentists, our goal is to select the option that preserves tooth structure, supports long-term function, and meets the patient’s esthetic goals.

Below is a clinical breakdown to help guide case selection and patient education

What Each Restoration Does

Veneers
Typically made of porcelain or composite, veneers cover:

  • The facial surface
  • The incisal edge (in most cases)

Primary Purpose:
Cosmetic enhancement — improving size, shape, alignment, and color with minimal tooth reduction.

Crowns
Made of porcelain, zirconia, or porcelain-fused materials, crowns cover:

  • The entire tooth (facial, incisal/occlusal, lingual, and all axial walls)

Primary Purpose:
Restore strength and structure when the tooth is compromised, while also improving aesthetics.

Before Either Option

From a dental education standpoint, it’s essential that:

  • Patients are over 18 (fully developed teeth, gums, and occlusion)
  • Orthodontics and/or whitening have been considered first when appropriate (Especially for spacing, rotation, and color concerns)

Key Similarities: Veneers vs Crowns

Both restorations:

  • Function as bonded coverings that require existing teeth (not replacements)
  • Typically involve 2 appointments spaced a few weeks apart
  • Require temporaries during the fabrication phase
  • Use local anesthesia
  • Can correct many of the same esthetic concerns:
    • Chips
    • Cracks
    • Gaps
    • Discoloration
    • Mild misalignment

Cost Comparison (U.S.)

Both porcelain veneers and porcelain crowns generally range $1,000–$2,000 per tooth, depending on:

  • Material
  • Lab
  • Geographic region
  • Provider experience

Strength & Durability

When bonded properly, both provide excellent long-term durability and allow patients to resume normal eating without concern.

Key Differences: Veneers vs Crowns

Tooth Structure Removal

  • Veneers: Minimal enamel reduction; conservative
  • Crowns: More aggressive reduction; circumferential and occlusal/incisal

Coverage

  • Veneers: Facial + incisal
  • Crowns: Full coverage (facial, lingual, incisal, and all axial walls)

Thickness

  • Veneers: Thin, typically 0.3–0.7 mm
  • Crowns: Thicker due to full coverage and strength requirements

Primary Indication

  • Veneers: Esthetic enhancement with structurally sound teeth
  • Crowns: Strengthening structurally weakened or heavily restored teeth

Clinical Decision-Making: When to Choose What

Veneers Are Ideally Used For:

  • Cosmetic improvements with minimal structural compromise
  • Mild-to-moderate alignment corrections
  • Improving proportions, shape, and symmetry
  • Discolorations or enamel defects
  • Wear cases limited to the incisal edge
  • Adults seeking stable long-term whitening without aggressive preparation

Goal: Maximum esthetics with maximum enamel preservation.

Crowns Are Indicated When the Tooth Is Structurally Compromised

Choose a crown when you see:

  • Fractures or cracked-tooth syndrome
  • Severe attrition/erosion
  • Large restorations covering multiple surfaces
  • Teeth with root canals
  • Significant rotation or malposition requiring major contour changes
  • Occlusal or bite corrections (crossbite, open bite, deep bite adjustments)
  • Teeth that already have existing crowns within the esthetic zone

Goal: Restore structural integrity first, then esthetics

Special Consideration: Smile Makeover Cases

Even in cosmetic cases:

  • A tooth with an existing crown must be restored with another crown
  • Teeth with large failing restorations or RCTs often require full coverage
  • A mixed case (some veneers, some crowns) is common and often ideal

High-end labs and proper occlusal planning can harmonize veneers and crowns beautifully in the
same smile.

Maintenance: Veneers and Crowns Share the Same Long-Term Care

Regardless of restoration type, patient instructions include:

  • Brush twice daily and floss once
  • Avoid biting hard objects (ice, popcorn kernels, hard candy)
  • Never use teeth as tools
  • Wear a night guard for grinding/clenching
  • Use a sports guard for athletic activities

With proper home care and follow-up visits, both can provide excellent longevity.

Clinical Bottom Line

Veneers

Best for esthetics with minimal prep when tooth structure is healthy.

Crowns

Best for strength, stability, and function when the tooth is structurally compromised.
Successful outcomes depend on one thing above all:
Proper case selection
.

Composite Veneers vs. Porcelain Veneers: What Dentists Need to Know

When patients ask about improving their smile, two of the most common restorative options you’ll discuss are composite veneers and porcelain veneers. While both can deliver excellent esthetics, the materials, workflow, longevity, and case indications differ significantly.
Understanding these differences and communicating them clearly is essential for proper case selection and patient expectations.
Below is a clinician-focused breakdown you can use chairside or in your practice education.

Composite Veneers vs Porcelain Veneers: The Key Differences

Cost Overview

  • Composite Veneers: $300–$800 per tooth
  • Porcelain Veneers: $1,500–$2,000 per tooth

Longevity

  • Composite: ~3–5 years on average
  • Porcelain: ~10–15+ years with proper care

Esthetics & Strength

  • Composite: Good esthetics but less durable; more prone to staining and wear
  • Porcelain: Superior esthetics, highest durability, highly stain-resistant

Chair Time

  • Composite: 1–2 visits
  • Porcelain: 2–3 visits (prep, provisionals, delivery)

Composite Veneers

When to Consider Composites

Composite veneers can be a good option when:

  • Teeth are already straight or close to ideal alignment
  • The patient wants to improve size, shape, or color without major positional changes
  • Budget is a significant factor
  • The patient prefers a reversible or minimally altered option

How They Work

Composite is directly bonded to the facial surfaces, sculpted chairside.
Most cases involve:

  • 10 upper teeth
  • Or 20 teeth for a full upper/lower enhancement

Cost & Treatment Timeline

  • $300–$800 per tooth
  • Typically 2 visits
  • Not covered by insurance

Sensitivity & Comfort

Minimal or no prep → little to no anesthetic required.
Patients generally tolerate the procedure extremely well.

Longevity & Maintenance

This is the biggest limitation.

  • Average lifespan: 3–5 years
  • Common issues: staining, chipping, edge wear, fractures
  • Requires regular polishing and periodic repairs

Clinical takeaway: Composites can be a good short-term or budget-friendly option, but durability and esthetics are not comparable to porcelain over time.

Porcelain Veneers

When to Consider Porcelain

Porcelain veneers are ideal when patients want to correct:

  • Misalignment
  • Spacing
  • Tooth size/shape discrepancies
  • Dark discolorations (tetracycline, trauma, fluorosis)
  • A more permanent white and esthetic transformation

This is also the go-to option for adults seeking long-term color stability.

How They Work

Thin ceramic shells are bonded to the facial surfaces after minimal enamel reduction. Most esthetic cases include:

  • 8–10 upper teeth
  • Or up to 20 teeth for full smile harmony

Cost & Treatment Timeline

  • $1,500–$2,000 per tooth
  • 2–3 visits: records → prep/provisionals → delivery
  • Not covered by insurance

Why the higher cost?
Porcelain veneers are:

  • Handcrafted by skilled ceramists
  • Highly individualized
  • A specialized, technique-sensitive procedure
  • Think of them as custom jewelry for the teeth.

Sensitivity & Comfort

Minimal enamel reduction done under local anesthetic.
Post-op sensitivity is typically mild and temporary.

Longevity & Durability

The biggest advantage of porcelain:

  • 10–15+ year lifespan
  • Exceptional stain resistance
  • Very low fracture or chipping rate

Clinical takeaway: Porcelain veneers are the most durable, esthetic, and long-lasting solution
for comprehensive smile design

Composite Bonding vs Veneers: A Quick Comparison for Dentists

FeatureComposite VeneersPorcelain Veneers
CostLowHigher
Visits1–22–3
Longevity3–5 years10–15+ years
Stain ResistanceLowExcellent
StrengthFairSuperior
SuperiorMinor shape/color estheticsMajor esthetic or structural improvements
Prep AmountMinimal–noneMinimal enamel reduction
MaintenanceHighLow

Clinical Bottom Line

Both materials have a place in modern cosmetic dentistry but they are not interchangeable.

  • Choose composite veneers for small esthetic enhancements, reversible options, or budget-sensitive patients.
  • Choose porcelain veneers for lasting esthetics, improved strength, smile transformation, and predictable long-term results.

Proper case selection, patient education, and setting clear expectations will ultimately determine the success and longevity of either approach.

Comparing Veneers vs. Orthodontics: A Clinical Guide for Dentists

Patients often ask whether they should straighten their teeth with braces/clear aligners or
improve their smile with veneers. As clinicians, the decision goes far beyond esthetics it’s
about diagnosing functional needs, case selection, and long-term stability.
Below is a dentist-focused comparison designed to help clarify when orthodontics is the
appropriate first-line therapy and when porcelain veneers may be the better solution

Braces vs. Veneers: What Dentists Should Consider

When Orthodontics Is Indicated

If a patient is satisfied with the size, shape, and color of their teeth but wants straighter
alignment, orthodontics remains the most conservative and predictable approach.
Braces or clear aligners should be strongly considered when patients present with:

  • Significant crowding
  • Generalized spacing
  • Rotations
  • Bite discrepancies (overbite, underbite, crossbite)
  • Skeletal concerns or jaw imbalance
  • For teenagers whose dentofacial structures are still developing orthodontics (often
  • combined with whitening later) is the ideal pathway

Types of Orthodontic Treatment

Traditional Braces
Metal brackets and wires bonded to the teeth, applying continuous forces to realign teeth.
Clear Aligners (e.g., Invisalign)
Removable trays worn 20–22 hours per day, sequentially advancing tooth movement.
Typical Orthodontic Details Dentists Should Know

  • Cost: $3,000–$7,000+ depending on complexity
  • Timeline: ~8 months to 24 months
  • Maintenance: Retainers required indefinitely
  • Discomfort: Short periods of soreness with activation or new trays
  • Insurance: Often partially covered

Orthodontics resolves foundational issues that veneers cannot and remains the gold standard for
bite correction.

When Porcelain Veneers Are Indicated

Porcelain veneers are ideal for adult patients who want to address cosmetic and proportional
issues beyond simple alignment.

Veneers can correct:

  • Mild–moderate misalignment
  • Small or worn teeth
  • Irregular contours
  • Persistent discoloration
  • Spacing
  • Asymmetry
  • Chips or fractures

They also provide a long-term whitening solution for patients who want a brighter shade that
does not require repeated maintenance.

Porcelain Veneers: Essential Clinical Details

  • Cost: ~$1,500–$2,000+ per tooth
  • Timeline: 2–3 visits over 3–5 weeks
  • Anesthesia: Local anesthetic recommended for comfort
  • Longevity: 10–15+ years with proper case selection
  • Insurance: Not covered
  • Post-op: Temporary sensitivity possible

Veneers offer immediate esthetic transformation and can address multiple concerns in a single
treatment modality — but they do not correct underlying bite issues.

Comparing the Two Options
What Orthodontics Does

  • Moves teeth into proper alignment
  • Improves occlusion and function
  • Addresses skeletal and structural problems
  • Provides conservative correction of spacing and crowding

What Veneers Do

  • Create the appearance of straighter, more symmetrical teeth
  • Correct color, shape, proportion, and smile design elements
  • Offer instant esthetic results
  • Provide stain-resistant, long-lasting outcomes

Treatment Considerations

  • Orthodontics is best for structural corrections and younger patients.
  • Veneers are ideal for adults seeking cosmetic improvement or a comprehensive smile
    makeover.
  • Combination therapy is often the most predictable: aligners or braces first, followed by veneers for proportional refinement.

Many adults finish orthodontic treatment only to realize they still don’t love their smile veneers can provide the final esthetic result they’re seeking

Advantages & Disadvantages: Clinically Summarized
Orthodontics — Advantages

  • Corrects occlusal and skeletal issues
  • Treats severe crowding or spacing
  • Improves functional stability
  • Covered by insurance in many cases

Orthodontics — Disadvantages

  • Longer treatment time
  • Retainer wear required indefinitely
  • Hygiene challenges with fixed appliances
  • Progress relies heavily on compliance with aligners

Porcelain Veneers — Advantages

  • Immediate esthetic transformation
  • Improves color, shape, proportion, and symmetry
  • Stain-resistant and long-lasting
  • Predictable esthetic outcomes in 2–3 visits

Porcelain Veneers — Disadvantages

  • Does not correct skeletal or major occlusal issues
  • Requires enamel removal (case-dependent)
  • Irreversible
  • Not covered by insurance

How to Choose the Right Path for Your Patient

The decision depends on:

  1. Functional needs
  2. Esthetic goals
  3. Tooth position and anatomy
  4. Timeline expectations
  5. Long-term maintenance
  6. Budget

For many cases, a staged approach (orthodontics → veneers) yields both functional stability
and the highest esthetic outcome